Retired child and adolescent psychiatrist and American expatriate in New Zealand. In 2002, I made the difficult decision to close my 25-year Seattle practice after 15 years of covert FBI harassment. I describe the unrelenting phone harassment, illegal break-ins and six attempts on my life in my 2010 book The Most Revolutionary Act: Memoir of an American Refugee.
Amnesty International is urging the NZ Government to rethink its approach to passing the COVID-19 Response (Vaccination) Legislation Bill due to serious concerns about the lack of opportunity for public consultation and scrutiny.
We have previously raised concerns about the lack of human rights scrutiny with the Government’s COVID-19 response, especially when introducing new legislation. Adequate scrutiny, particularly for mandatory measures, is essential for both enduring and effective people-centred solutions, as well as maintaining the rule of law.
“We are deeply concerned to see limited scrutiny of yet another piece of legislation with significant human rights implications.”
Lisa Woods, Campaigns Director, Amnesty International Aotearoa New Zealand
Amnesty International encourages the Government to place human rights at the centre of all aspects of its response. Rushing through law is not the way to ensure appropriate safeguards, especially when that legislation limits human rights.
We welcome the Government’s recognition of the need to pursue robust, crucial measures that urgently stop the spread of COVID-19. The Government has an obligation to protect the rights to health and life. However any limitations on human rights must meet the principles of legality, legitimacy, necessity and proportionality, and non-discrimination. Evidence of this must be transparent and open to the public.
The Government needs to ensure the Bill includes a range of safeguards, including a clear aim and justification, a specified and limited timeframe, and precise wording on how it will be implemented.
The latest reports from the mainstream media admit that the pandemic is basically non-existent in Africa, which is confusing to those who believe the narrative that the jabs are helping to eradicate disease.
No media draws the correlation between low vaccine injury and low vaccine numbers
from Truth 11, shared with thanks
Few people in Africa are getting “vaccinated” for theCovid-19, and as a result there is almost no covid anywhere to be found on the continent.
Ironically, the racist capitalist patenting and hoarding of western Covid vaccines may have saved millions of Africans from a terrible death, although the hypocritical campaign to SAVE AFRICANS by selling the expensive vaccines is still gearing up.Covid-19 vaccine tracker: View vaccinations by country
The latest reports from the mainstream media admit that the pandemic is basically non-existent in Africa, which is confusing to those who believe the narrative that the jabs are helping to eradicate disease.
A recent piece from the Associated Press (AP) explains that in Zimbabwe, nobody wears a mask, nobody is vaccinated, and life goes on as normal. People pack the local markets…
Vancouver reporting 13 stillbirths in 24 hours. Waterloo Ontario reports 86 stillbirths (all fully vaccinated mothers) between Jan-July 2021 (normal average is 6 per year).
Benjamin begins this lecture around 1500 BC, when Indo-Aryans from northern Asia invaded the Indus Valley civilization. They battled with indigenous Dravidians for 500 years. Eventually they abandoned their nomadic way of life for a sedentary lifestyle, assuming control of most of India as a new ruling elite.
The Rig Veda, a sacred text of the Hindu religion, comes out of this period. From 1000 BC on, the population of India was divided into four varas (Sanskrit for color):*
Brahmans – priests
Kshartryas – nobles and warriors
Varshyas – artisans and merchants (ie commoners)
Sidras – serfs
“Untouchables,” the fifth vara was added later. “Untouchables” performed unclean work and touched dead animals (tanners and butchers).
In the 7th century BC, a radical Brahman sect emerged that embraced mysticism, yogic meditation and reincarnations. They recorded their teachings in the Upanishads. Jainism and Buddhism emerged about a century later.
Jainism, which teaches that all living beings (including plants and insects) have a soul and forbids any form of violence. The Jains rejected caste systems and lived extremely ascetic lives.
Buddhism, founded by Siddhārtha Gautama during the 6th century BE, also rejected caste systems but were less ascetic than the Jaines. Initially more a philosophy than a religion, Buddhism teaches that renouncing desire and rampant ambition is the only way to end human suffering. Because Siddhārtha and his disciples taught in local dialects, rather than Sanskrit, his teachings quickly spread throughout India, China, Japan, Korea and elsewhere in Southeast Asia.
Eventually the entire Indus Valley was broken up into city-states, with each having its own maharaja (king). Villages surrounding the city-states were self governing with elected village committees.
Women had virtually no rights. They could only be in public with a male protector and were were forbidden to participate in religious life (except as nuns). After 500 BC, widows were expected to practice Suti (ie leaping into their husband’s funeral pyre).
Between 522 and 486 BC, the Persians expanded their empire into the Indus Valley and occupied much of modern day Pakistan.
Alexander the Great liberated the Indus Valley when he conquered Persia. Once Alexander withdrew (322 BC), Chandragupta Maurya united most northern India city-states into a single state. The Mauryan empire engaged in irrigation agriculture, manufacturing, road construction, timber harvesting, cattle breeding and inter-indregional trade.
Following the death of Chandragupta’s son Ashoka in 232 BC, the Mauryan empire began to decline. It collapsed in 185 BC, with northern and southern India breaking into separate regional city-states.
*After the Portuguese colonized India in the 16th century, the word “caste” was adopted from the Portuguese word “castas”)
The film can be viewed free with a library card on Kanopy
The American Heart Association Journal has released a report showing something that may not alarm our readers. According to researchers, COVID19 vaccines increase the likelihood of a cardiac event.
Emphasis mine.
“We conclude that the mRNA vacs dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.”
This coincides or confirms that reporting we’ve shared on a number of fronts, including athletes at all levels who have been vaccinated, suffering cardiac events, or dying of heart attacks, often during competition.
Abstract 10712: Mrna COVID Vaccines Dramatically Increase Endothelial Inflammatory Markers and ACS Risk as Measured by the PULS Cardiac Test: a Warning
Our group has been using the PLUS Cardiac Test (GD Biosciences, Inc, Irvine, CA) a clinically validated measurement of multiple protein biomarkers which generates a score predicting the 5 yr risk (percentage chance) of a new Acute Coronary Syndrome (ACS). The score is based on changes from the norm of multiple protein biomarkers including IL-16, a proinflammatory cytokine, soluble Fas, an inducer of apoptosis, and Hepatocyte Growth Factor (HGF)which serves as a marker for chemotaxis of T-cells into epithelium and cardiac tissue, among other markers. Elevation above the norm increases the PULS score, while decreases below the norm lowers the PULS score.The score has been measured every 3-6 months in our patient population for 8 years. Recently, with the advent of the mRNA COVID 19 vaccines (vac) by Moderna and Pfizer, dramatic changes in the PULS score became apparent in most patients.This report summarizes those results. A total of 566 pts, aged 28 to 97, M:F ratio 1:1 seen in a preventive cardiology practice had a new PULS test drawn from 2 to 10 weeks following the 2nd COVID shot and was compared to the previous PULS score drawn 3 to 5 months previously pre- shot. Baseline IL-16 increased from 35=/-20 above the norm to 82 =/- 75 above the norm post-vac; sFas increased from 22+/- 15 above the norm to 46=/-24 above the norm post-vac; HGF increased from 42+/-12 above the norm to 86+/-31 above the norm post-vac. These changes resulted in an increase of the PULS score from 11% 5 yr ACS risk to 25% 5 yr ACS risk. At the time of this report, these changes persist for at least 2.5 months post second dose of vac.We conclude that the mRNA vacs dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.
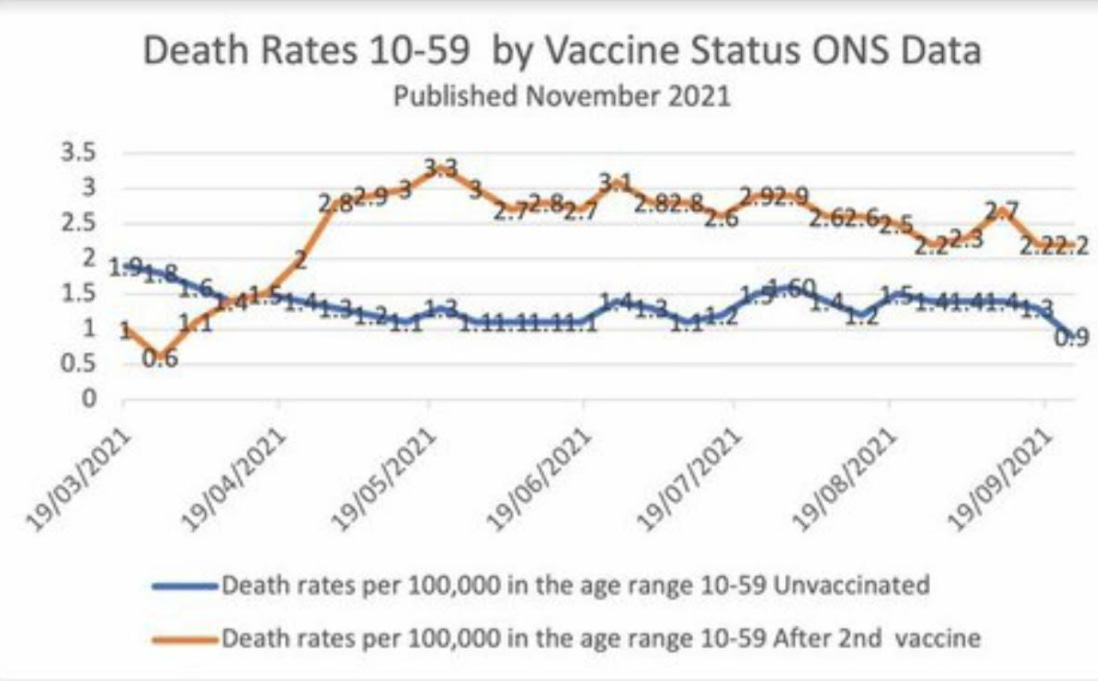
And have been for six months. This chart may seem unbelievable or impossible, but it’s correct, based on weekly data from the British government.
The brown line represents weekly deaths from all causes of vaccinated people aged 10-59, per 100,000 people.
The blue line represents weekly deaths from all causes of unvaccinated people per 100,000 in the same age range.
I have checked the underlying dataset myself and this graph is correct. Vaccinated people under 60 are twice as likely to die as unvaccinated people. And overall deaths in Britain are running well above normal.
I don’t know how to explain this other than vaccine-caused mortality.
The basic data is available here, download the Excel file and see table 4:
It was Hillary all along. The indictment by Special Counsel John Durham of Igor Danchenko for lying to the FBI demonstrates conclusively the Steele dossier was wholly untrue. Clinton paid for the dossier to be created and Clinton people supplied the fodder. Steele, working with journalists, pushed the dossier into the hands of the FBI to try to derail the Trump campaign. When that failed, the dossier was used to attack the elected president of the United States. The whole thing was the actual and moral equivalent of a Cold War op where someone was targeted by the FBI with fake photos of them in bed with a prostitute.
Start with a quick review of what Durham uncovered about the most destructive political assassination since Kennedy.
Christopher Steele, paid by the Clinton campaign (after Clinton’s denial, it took a year for congressional investigators to uncover the dossier was commissioned by the opposition research firm Fusion GPS, working for the Democratic Party and Hillary Clinton’s campaign, paid through the Perkins-Coie law firm) did no investigative work. Instead, his reputation as a former British intelligence officer was purchased to validate a dossier of lies and then to traffic those lies to the FBI and journalists.
Durham’s investigation confirms one of Steele’s key “sources” is the now-arrested Danchenko, a Russian émigré living in the U.S. Steele was introduced to the Russian by Fiona Hill, then of the Brookings Institute (Hill would go on to play a key role in the Ukraine impeachment scam.) Danchenko completely made up most of what he told Steele about Trump-Russian collusion. What he did not make up himself he was spoon fed by Charles Dolan, a long-time Clinton hack and campaign regular. Ironically, Dolan had close ties not only to the Clintons but to the Russians as well; he and the public relations firm where he worked represented the Russian government and were registered as foreign agents for Russia. Dolan is credited with, among other things, making up the pee tape episode. Dolan also fed bogus info to Olga Galkina, another Russian who passed the information to Danchenko for inclusion in the dossier. Galkina noted in e-mails she was expecting Dolan to get her a job in the Hillary administration. Steele, a life-long Russia and intelligence expert, never questioned or verified anything he was told.
In short: Clinton pays for the dossier, Steele fills it with lies fed to him by a Clinton PR stooge through Russian cutouts, and the FBI swallowed the whole story. There never was a Russiagate. The only campaign which colluded with Russia was Clinton’s. And Democrats, knowing this, actually had the guts to claim it was Trump who obstructed justice.
The American Medical Association reported that 96% of U.S. doctors were vaccinated in June. Even with a 20-point error margin, accounting for saline/placebo shots and exemptions, a vast majority of doctors have received the shots. It’s only fair since doctors peddle the injections to their unwitting, credulous fanatics who worship the white coats.
Vaccines are the leading cause of coincidences. We all know that. But you can literally search keywords like “died suddenly” and “died unexpectedly” in Yahoo, Bing, DuckDuckGo, etc. and find endless stories like the following. Booster shots commenced on September 22. That could also be a coincidence. But all of the following doctors died on October 13 or later.
We could literally include 100 doctors in this story if time permitted. All of these happened in the last four weeks. The youngest is 32. The oldest is 59.
Dr. Kevin Walsh – Roanoke, Virginia
WDBJ 7 in Roanoke reported that Dr. William Kevin Walsh passed away “suddenly” and “unexpectedly”on October 29 at the age of 51. He was an OB-GYN with a private practice. Dr. Walsh was also affiliated with LewisGale Medical Center. He is survived by his wife and five children.
Dr. Walsh advocated for “vaccines” and equated COVID-19 to polio on Facebook just six weeks before his death.
Dr. Justin Nasser – Benowa, Queensland (Australia)
It’s not just happening in the United States. Dr. Justin Nasser “died unexpectedly of a heart attack” on November 14, according to the Gold Coast Bulletin. He was 52 years old. The Bulletin also described his death as “sudden.” Dr. Nasser was an OB-GYN at Gold Coast University Hospital and medical director of Swell Women’s Ultrasound. He is survived by his wife and three children.
Dr. Stephanie Allison Bosch died “suddenly and unexpectedly” of a pulmonary embolism on October 13, according to Yachats News. She was just 32 years old. Dr. Bosch finished her residency just three years ago. She was a general practitioner at Samaritan Waldport Clinic since 2018. Dr. Bosch is survived by both parents and several siblings.
Dr. Craig Michael Shannon passed away at his home on October 29. He was 42. Dr. Shannon was a neurosurgeon at Vassar Brothers Medical Center in Poughkeepsie. He was apparently well-liked by his patients, as you cannot find one negative thing about him online.
The U.S. Second Circuit Court of Appeals upheld the New York vaccine mandate for healthcare workers on November 4. The Court denied the Petitioner’s motion for preliminary injunction. The two original cases are remanded back to their respective lower courts to litigate the cases’ merits. All New York healthcare workers were required to be “fully vaccinated” by October 7.
Two different obituaries imply that Dr. Shannon died from non-Hodgkin lymphoma. But he died in his home. If he had advanced, aggressive non-Hodgkin lymphoma, he would have died in a hospital or in hospice, not at home. Dr. Shannon is survived by his wife and both parents.
Dr. Elliott Gagnon – Wasilla, Alaska
Dr. Elliott Gagnon “passed away unexpectedly at his home” on October 14, according to the Mat-Su Valley Frontiersman. He was 48. Dr. Gagnon was a plastic surgeon with his own private practice. He was also affiliated with Mat-Su Regional Medical Center.
We are not giving individual medical advice. These are our personal views. People should check the government website to obtain a range of views. We are not being paid or influenced to be here.
I graduated in 1993 and worked in an Emergency Department until GP training in 2009. I became a Fellow of the College of GPs in 2013. I have done additional training in lifestyle medicine and I understand the power that nutrition, exercise, sleep and stress management can have over our health, including prevention and treating chronic disease and reducing vulnerabilities to infectious disease. Most doctors have not trained in these areas and are unaware of the power of lifestyle interventions.
From the start of the pandemic, I had concerns about the New Zealand response. There was no focus on health creation and noone was counting the cost of the measures imposed on the population. We only heard from a few academics, most of whom were not working in clinical areas. I listened to these local experts and found them lacking, so in addition I have spent probably over 1500 hours listening to and learning from a range of overseas experts in a variety of fields. This includes practising physicians in ICU, Emergency departments, cardiology, General Practice, as well as scientists, vaccine developers, immunologists, virologists, pathologists and others.
I tried to engage in questions and discussions in the limited available medical forums but was mostly ignored or fobbed off with partial answers. It became obvious as 2020 progressed, that the goal was a vaccine and treatment was not part of the agenda. Strict containment measures were required until everyone could be offered a vaccine.
Early in 2021 I felt increasingly uncomfortable about the inexorable push for a vaccine to the exclusion of all else. I was also concerned about the proposed use of a new technology on such a wide scale, the short length of the clinical trials and the small numbers of participants used to provide interim data that the national program was based upon. Also about the fact that Medsafe had a lot of unanswered questions even as the rollout began, the lack of liability for the drug company, and the continued lack of discussion about anything else.
The marketing campaign began and the only message was “get vaccinated, it’s safe and effective”.
I was disturbed that noone in the medical profession except Dr Simon Thornley was asking questions. Trying to engage with the profession got me nowhere, so I felt compelled to speak to the public. I spoke on a PlanB webinar in October 2020 to voice my questions. A significant number of members of the public shared my concerns. I have continued to speak, even though I am more comfortable having individual medical discussions with patients.
Assumptions:
1. We are in the middle of a pandemic of a deadly disease;
2. The PCR test is a valid diagnostic tool;
3. Nothing other than mass vaccination can be done.
All of these assumptions should be debated and challenged.
I have a document from the Ministry of Health which includes a sentence that “Most people experience mild illness and recover completely using symptomatic and supportive treatments for viruses such as rest, fluids and anti-fever medication”. The public has been made to think that if they catch Covid-19 they are going to die. Nothing could be further from the truth. The vast majority of people, including the elderly and infirm, will survive.
Some people will die but they are mostly people already in their last year or two of life. Those people might want to be surrounded and supported by their loved ones at the end of their lives, rather than be left scared and alone. The average age of death from Covid-19 is 82 years, which is older than the average life expectancy.
The survival rate for our children and young people less than 29 years old, is 99.986% without vaccines or treatment. There is the possibility of Long Covid, but I don’t have a clear idea of how many people that is likely to affect and whether early treatment reduces the chances of that occurring.
Nigeria, Sierra Leone, Bolivia, Paraguay, Peru, Guatemala, Honduras, Macedonia, Uttar Pradesh, India, Zimbabwe, the Czech Republic, Slovakia, parts of Brazil, and other nations have the following in common:
They use known safe and effective ivermectin for treating and curing flu/covid.
As a result, the incidence of the viral illness in these countries is low.
Their success is in stark contrast to surging outbreaks, serious cases, hospitalizations and deaths throughout the US/West, Israel and in other heavily mass-jabbed countries.
Since discovered and approved for human use, around 4 billion doses of ivermectin have been prescribed worldwide.
The WHO includes it on its list of Essential Medicines.
In 2015, co-developer of the drug, Dr. Satoshi Omura, won a Nobel Prize in Medicine.
In February, British Ivermectin Recommendation Development (BIRD) — comprised of medical and scientific experts from over 15 countries — recommended global use of ivermectin as a verifiably safe and effective drug for preventing and treating flu/covid.
Evidence-Based Medicine Consultancy director and BIRD organizer Dr. Tess Lawrie stressed the following:
“Ivermectin is already in use around the world and can reach the poorest people long before other expensive COVID treatments will ever get to them.”
“Ivermectin has an ever-increasing evidence base that shows that it works.”
“Even the prestigious Institute Pasteur in France has confirmed that the evidence is sound.”
Front Line (Flu/Covid) Critical Care Alliance (FLCCC) president/chief medical officer Dr. Pierre Kory explained the following:
“When we examine the extensive evidence on ivermectin as a treatment for (flu/covid), we still see a significant reduction in the spread of (the viral illness), as well as a reduction in hospitalizations and deaths. All science needs to be scrutinized. As some of the most published researchers in our fields, we are used to having our work examined by others.”
Peer-reviewed studies showed that when used as directed, ivermectin virtually eliminates flu/covid, most often in a few days.